FirstSpear

Archive for the ‘Medical’ Category

Army Nears Crucial Brain Health Testing Milestone

Tuesday, September 29th, 2026

WASHINGTON — About 97 percent of Soldiers have taken the Neurocognitive Assessment Tool assessment, helping medical professionals combat the effects of blast overpressure and low-level blast exposure, the Army’s top leader overseeing safety and occupational health said.

“It demonstrates our commitment to cognitive safety, medical readiness and warfighting capability,” said Assistant Secretary of the Army for Installations, Energy and Environment Jordan Gillis.

The War Department established NCAT as a required cognitive baseline assessment to monitor and track Soldier brain health and support recovery of traumatic brain injuries.

Soldiers in impacted career fields, including those operating heavy weapons systems such as field artillery, combat engineers and explosive ordnance disposal technicians, must take the assessment under a War Department directive.

Troops in these fields must take the NCAT upon entering the military, before deployment and following an injury or suspected concussion. The Army requires Soldiers in high-risk military occupational specialties to complete the assessment annually and for all Soldiers to take the test every three years.

According to studies published by the National Institutes of Health, continuous exposure to blast shockwaves has been linked to TBI.

Gillis, as the Army’s Designated Agency Safety and Health Official, or DASHO, oversees the Army’s safety and occupational health program.

The NCAT is just part of a broader overpressure program that the Army will soon publish in a service wide directive, Gillis said. The core tenets of the program include hazard assessment, risk assessment and exposure tracking, risk mitigation, cognitive monitoring, information management, illness and injury reporting, and training and education.

The Army identified blast overpressure and low-level blast exposure as critical occupational safety and health hazards.

“It affects everyone differently,” Gillis said. “The takeaway is we are trying to take care of Soldiers and monitor their health. And if there is an impact, we’ll be able to treat them.”

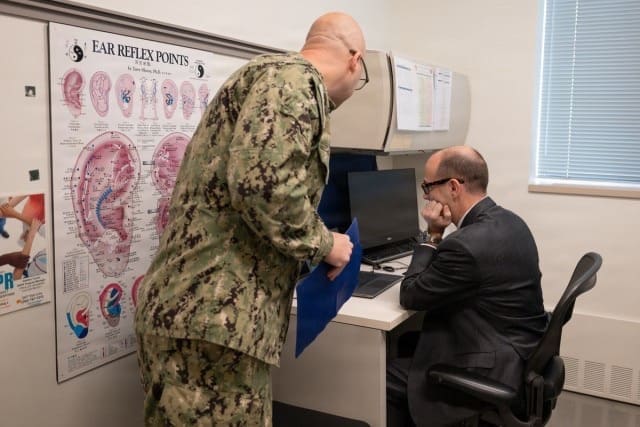
Soldiers from across the force on active duty and in the Army National Guard and Army Reserve must complete the NCAT; they began taking it in 2024. To further set an example for Soldiers, Gillis took the NCAT test himself at the Pentagon Special Missions Auxiliary Clinic on Sept. 18.

“This was the perfect time to be wearing both my DASHO hat and my Army Reserve hat and to meet the requirement that I have in the Reserve but also set the example for everyone across the force,” he said.

Gillis, a lieutenant colonel in the Army Reserve, serves as a field artillery officer, which places him in the high-risk category for blast overpressure effects.

During his years on active duty, he suffered injuries while deployed in support of Operation Enduring Freedom, for which he received a Purple Heart and a Bronze Star Medal. He knows firsthand the impact of exposure to heavy weapons firings and improvised explosive devices.

“I am from the era of Soldiers who grew up in the height of the global war on terror, and many of us were exposed to blast overpressure through things like IED attacks,” Gillis said. “I myself experienced several IED attacks, and so I believe from personal experience that this is important to do.”

Gillis said managing Soldier cognitive health and preventing potential traumatic brain injury and side effects remains a top readiness priority.

“[The NCAT] is an important part of taking care of Soldiers, but what this does is, it sets a baseline for reaction times and for memory,” he said. “By establishing a baseline for all Soldiers, we’re able to monitor brain health, as well as … let medical providers help with treatment, if required.”

By Joe Lacdan, War Media Activity

The Medical Kit You Stopped Knowing Why Familiarity and Readiness Fade Long Before the Emergency

Monday, September 28th, 2026

The Problem on the Pavement

I arrived at the crash a few minutes behind another officer.

His trauma kit was already open on the pavement. Gauze wrappers moved in the wind and caught against the edge of the road. Under the rotating emergency lights, he dug through the pouch, lifting one item after another and putting each one back as if the answer might be underneath it.

The patient was nearby. The ambulance was still miles away.

The officer was not panicked. He was not frozen.

He was lost.

The kit had been issued years earlier. He had trained with it once, mounted it to his equipment, and carried it through countless shifts without opening it again. Now, kneeling on the shoulder of a rural road, he had equipment in front of him but no working familiarity with what it contained.

This was not a tactical incident. It was an ordinary car crash, the kind that happens every day in communities where professional medical help may still be fifteen or twenty minutes away.

The officer carried the kit.

What he no longer carried was familiarity.

Nothing about that scene was unusual. In fact, it represents one of the most common medical-readiness gaps I encounter, and it has very little to do with the quality of the equipment inside the pouch.

The kit was present.

Readiness was not.

When Presence Becomes a Substitute for Capability

Somewhere between issue day and the emergency, a trauma kit can stop being working equipment and become a symbol.

The officer knows it is there. The pouch occupies the same place on a carrier, duty belt, or inside a patrol vehicle. Its presence creates reassurance, and over time, that reassurance begins to stand in for capability.

The kit gets mounted and forgotten.

Inspections come and go. Elastic stretches. Supplies expire. Someone borrows an item and does not replace it. A tourniquet staged incorrectly on day one may remain that way for years because nobody opens the pouch and questions it.

The equipment still looks ready from the outside.

That is what makes the problem dangerous.

Carrying medical equipment is not the same as maintaining medical capability.

Capability has an expiration date when it is not renewed.

Training Does Not Remain Fresh Because the Certificate Does

Almost every officer I meet has received medical training.

Far fewer have received it recently.

There was an academy block, a certificate, and a successful evaluation. The officer demonstrated the required skills, returned to duty, and moved on to the next responsibility.

Then the years began to pass.

The certificate does not change.

The responder does.

Knowledge becomes less immediate. Confidence remains even as fluency declines. Five years may pass before an emergency finally asks whether the skill is still usable.

That is a brutal time to discover the answer.

Medical intervention is especially vulnerable to decay because it requires judgment and action at the same time. Applying a tourniquet, packing a wound, managing an airway, or assessing a casualty are not simply physical tasks. They require decisions made under stress.

The responder still remembers taking the course. The steps may still sound familiar when someone explains them.

But recognition in a classroom is different from performance beside a damaged vehicle in poor light while another person waits for help.

Skill does not need to disappear completely to become insufficient.

It only needs to fall below the level the emergency demands.

The Emergency May Not Match the Kit

The officer at that crash faced another challenge.

His kit had been assembled primarily for penetrating trauma. It contained a tourniquet, hemostatic gauze, and a chest seal. For a gunshot wound, those items may have been exactly what he needed.

That was not the emergency in front of him.

Patrol officers routinely encounter vehicle crashes, falls, overdoses, industrial injuries, medical emergencies, and prolonged waits for EMS. There is nothing wrong with carrying a specialized trauma kit. The problem begins when responders expect one specialized solution to solve every problem.

Training reveals what equipment is missing, what equipment is unnecessary, and what emergencies are most likely to occur in a particular community.

The requirement should drive the equipment.

The equipment should not be purchased first and justified later.

Sustainment Training Reveals the Truth

Sustainment training does more than preserve skill.

It diagnoses readiness.

You cannot identify weaknesses in equipment you never open. You cannot evaluate skills you never test. You cannot know whether a medical system works under pressure by looking at it mounted neatly on a duty belt.

Realistic repetitions expose gaps quickly.

Missing supplies become obvious. Poor placement becomes frustrating. A kit that seemed organized becomes confusing when opened in low light. Equipment that seemed easily accessible becomes difficult to reach from a vehicle seat.

Those discoveries should be welcomed.

A failure discovered during training is a problem that does not have to be discovered beside a real casualty.

Without those repetitions, readiness is based on memory and assumption.

Sustainment training replaces assumption with evidence.

A Practical Sustainment Standard

Maintaining familiarity does not require a major budget increase or a dedicated training day. It requires consistency.

• Inventory the kit from memory.

• Open and inspect it quarterly.

• Practice access under realistic conditions.

• Train for the emergencies you are most likely to encounter.

• Put sustainment training on the calendar.

Familiarity is perishable. Like any other critical skill, it must be renewed deliberately before it is needed.

Five Questions Worth Answering Now

Before purchasing another piece of equipment, answer these questions honestly:

1. When was the last time you opened your medical kit and handled its contents under pressure?

2. Can you identify everything inside it right now without looking?

3. Can you access the kit and deploy the tourniquet using only your support hand while seated and in low light?

4. What emergency was the kit originally built to address, and what emergencies do you encounter most often?

5. If you had to work from a partner’s kit instead of your own, could you use it effectively?

If those answers create discomfort, pay attention to it.

Discomfort is information.

It means a gap has been identified before an emergency exposed it.

Know the Kit Before the Kit Is Needed

I still think about the officer kneeling on that rural road.

The gauze wrappers moving across the pavement. The open pouch beneath the emergency lights. The ambulance somewhere in the distance. The officer holding equipment that had been beside him for years but had become unfamiliar when he finally needed it.

Nothing inside that pouch had suddenly changed.

The distance between the officer and the equipment had grown one unopened shift at a time.

Somewhere tonight, another trauma kit is sitting untouched on a duty belt, mounted to a carrier, stored inside a patrol vehicle, or tucked behind the seat of a truck.

Its owner may have carried it for years.

Maybe that confidence is justified.

There is only one honest way to find out.

Open the kit.

Lay out the contents.

Train with the equipment until every item has a purpose, every position is familiar, and every movement has been practiced before urgency takes control of the moment.

The solution may not be another purchase.

It may be an afternoon of repetitions, a training partner, and the willingness to confront what has faded.

Do it before gravel is beneath your knees, blood is on your gloves, and the ambulance is still miles away.

Do it before somebody else’s life depends on what you remember.

Learn More About Blue Force Gear® Medical Solutions

Familiarity should never begin while kneeling beside a casualty.

Whether you’re evaluating an existing setup or building a medical capability from the ground up, Blue Force Gear’s trauma kits are designed to provide rapid access, consistent placement, and secure organization so responders can focus on the problem in front of them, not the equipment on their belt.

Explore the Micro Trauma Kit NOW!® Nano ES, and the full line of Blue Force Gear trauma kit solutions.

This article is intended for general educational purposes and is not a substitute for certified medical training, agency protocols, product instructions, or guidance from qualified medical professionals.


By John Chapman, Task Force 70 Foundation

About the Author

John Chapman, known widely as Chappy, is a law enforcement professional with more than 34 years of experience spanning operations, leadership, curriculum development, applications engineering, and training. A published author and nationally recognized instructor, he has spent nearly three decades developing and delivering patrol and tactical law-enforcement training programs.

Chappy currently serves as Executive Director of the Task Force 70 Foundation, a nonprofit dedicated to training, mentoring, and supporting underserved rural and small-town law-enforcement agencies throughout the United States.


US Navy Awards Aware $10M Sole-Source Program of Record

Monday, September 14th, 2026

Aware Awarded Sole-Source U.S. Navy Program of Record for Advanced Custom Hearing Protection Solutions Precision-Engineered from Its Proprietary 3D Ear Scanning Technology

Atlanta, GA – September 14, 2026 – Aware Defense, a leader in custom in-ear devices powered by its proprietary eFit 3D ear scanning technology and a division of Aware CBW, has been awarded a sole-source Program of Record contract by the Naval Air Systems Command’s Aircrew Systems Program Office (PMA-202) to advance hearing protection. This prestigious selection underscores Aware’s innovative technology and commitment to protecting the warfighter.

“We are honored to be chosen as the sole-source supplier for this critical program to deploy custom hearing protection built from each warfighter’s unique ear anatomy using Aware’s patented 3D ear scanning technology,” said Sam Kellett, Jr., Chief Executive Officer of Aware.

“Hearing loss is one of the most common service-connected disabilities, and it is preventable. Because every ear is different, our eFit scanner and advanced additive manufacturing deliver precision-built protection and communications for mission-critical environments, custom fit at scale. This award reflects the U.S. Navy’s commitment to preventing hearing loss and sets a new standard for protecting the warfighter.”

The five-year contract establishes Aware Defense as the U.S. Navy’s exclusive end-to-end source for 3D digital ear scanning to capture ear canal geometry, manufacture custom hearing protection and Communications Earplugs (CEP), and deliver devices precision-engineered to the individual ear anatomy of Naval Aviation aircrew and flight-line maintainers. The PMA-202 program is anchored by Aware’s eFit scanner, the only non-contact optical 3D scanning system that uses radial illumination to capture the true geometry of the ear and ear canal past the second bend with dimensional accuracy of less than 90 microns.

The sole-source contract builds on proven execution and field validation. Under initial program funding, Aware Defense conducted on-site 3D ear scanning events nationwide and delivered 6,373 custom-fit devices from September 2025 to July 2026, while working alongside NAVAIR Aeromedical Safety Officers and Navy audiologists to fit service members. Under PMA-202, Aware will scale to 42,000 custom-fit units starting August 1, 2026, at Naval Air Stations across the United States (CONUS) and overseas (OCONUS).

“Aware Defense is ready to execute at fleet scale,” said Stu Booker, President of Aware Defense.

“We are proud to continue our partnership with the Navy to accelerate the fielding of advanced hearing protection. We know that gear that fits gets worn, and every ear scan and custom-fit device advances our mission to protect warfighters and preserve long-term hearing health. Our team has proven its ability to seamlessly scan 700 personnel in five days and have precision-fit devices in the warfighters’ ears within 60 days, enabling rapid program expansion across Naval Aviation.”

Hearing loss remains one of the most common and costly injuries across the Department of Defense. With Aware Defense’s Program of Record, custom hearing protection will become integral to how the U.S. Navy protects the hearing of its aviation personnel while supporting clear communications and operational readiness.

www.awaredefense.us

Veteran Wellness Podcast

Sunday, September 13th, 2026

The Veteran Wellness Podcast is hosted by my friend Erik Lawrence who speaks with fellow Veterans about service, health, and life.

His inaugural video was launched today and features Retired Green Beret Scott LaMorte.

Expect an honest conversation about military service, combat injuries, traumatic brain injury (TBI), cancer, recovery, and the mindset that helped carry Scott through some of life’s toughest challenges.

Scott reflects on the injuries he sustained in Afghanistan, his cancer diagnosis, the treatments and wellness approaches he chose to pursue, and why he believes faith, resilience, and taking an active role in his own health became central to his recovery.

Special Operations Forces Tackle Unseen Threat of Blast Exposure

Tuesday, September 8th, 2026

The U.S. special operations forces community is actively tackling the invisible threat of repeated blast overpressure to protect warfighters’ brain health without compromising combat readiness.

This is important since, in just six months of initial entry training, a SOF soldier will fire thousands of small arms rounds, employ hundreds of flash-bang devices, and conduct dozens of explosive breaches. For these operators, low-level blast exposure of less than four pounds per square inch is not a rare incident, but rather a daily, unavoidable reality of their training and operational environments. 

Managing this risk factor presents a massive challenge. The scientific community suspects that cumulative, repeated blasts could cause long-term cognitive effects, yet there are currently no validated thresholds to guide medical decisions or return-to-duty timelines.  

Simply tracking the blasts is a logistical hurdle because current sensors are often bulky, competing for precious space on an operator’s mission-essential gear. Furthermore, vendor data rarely synchronizes smoothly with standard military systems, and there is little agreement on how peak pressure and incident pressure meaningfully accumulate. 

“More importantly, current sensors only measure the blast wave itself, leaving a critical human gap with no event-linked cognitive, physiological or biomarker data for the operator standing in its path,” said Army Sgt. Maj. Chris McNamara, 3rd Operations Support Group human weapon system director. 

To bridge these scientific and operational gaps, the SOF community launched aggressive, data-driven initiatives like the Elite Force Pilot Team. 

“This specialized task force is evaluating how to implement high-fidelity monitoring during high-risk training and operations,” McNamara said. “Their goal is to ultimately standardize how leaders make risk and readiness decisions.”

The objectives of the pilot team are to mitigate effects of blast overpressure by monitoring high-risk training and operations. They have used lessons learned to improve return-to-duty and return-to-shoot protocols and correlate blast overpressure to clinical outcomes by using evidence-based biomarkers. 

McNamara highlighted the operational reality of these efforts, noting that a delicate balance exists between collecting timely data and not disrupting the tempo of training. He emphasized the essential need to identify accurate and nonintrusive methods for collecting data on blast exposure, cognitive performance and biomarkers.

“As the scientific community strives to find clarity in exposure measurement, leaders at all levels must simultaneously be equipped with relevant and effective risk-mitigation tools,” said Kathy Lee, director of warfighter brain health policy at the Office of the Assistant Secretary of War for Health Affairs.

Instead of waiting for universal medical standards to be finalized, SOF leaders are already implementing physical changes to training and equipment. One innovation is the multiuse charge housings for enhanced target effect, a flexible charge housing designed to optimize breaching operations while safeguarding service members.

Made of nontoxic, inert materials, the system is dual purposed for sheet explosives and detonation cords. By using advanced 3D computer modeling and wave-shaping design techniques, the housing focuses blast energy toward the target, allowing for a lower net explosive weight. This optimization delivers identical target-defeat capabilities while reducing hazardous blast overpressure on the warfighter by 25-60%.

The system is highly intuitive, significantly reduces charge preparation, builds time to maximize training efficiency and is currently being positioned for expanded military distribution.

“Our priority is to field technology that treats the operator as our premier weapon system,” said Chris Wilson, division lead for human weapon system at the U.S. Special Operations Command’s Science and Technology Directorate. “Innovations like [the housing] prove we don’t have to choose between lethality and safety. By using advanced engineering to shape the blast physics, we are actively lowering the physical toll on the human weapon system while keeping our operators sharp, lethal and in the fight longer.”

For SOF members, the firing ranges and facilities are being redesigned based on advanced modeling of blast waves. New construction materials are also being used that absorb shockwaves.

Operators are also seeing improvements in their standard gear. This includes the increased use of updated weapon suppressors, heavy weapon simulators and strict helmet policies.

Researchers are even using biometric instrumented head forms to measure exactly what happens inside a helmet during a blast, leading to improved helmet padding systems. For industrial hygiene monitoring, new hard-copy and mobile applications are being developed to streamline the recording of blast overpressure data directly in the field.

Ultimately, the overarching warfighter requirement remains clear: a low-burden sensor with integrated power and interoperable data that clinicians can actually use to monitor health.

By taking decisive action today, U.S. Special Operations Command is taking proactive steps to improve brain health, detect early warning signs and implement preventive measures to extend operational longevity, enhance mission readiness and ensure the long-term health of SOF warfighters.

By Derik Crotts, Office of the Assistant Secretary of War for Health Affairs

Air Force Global Strike Command Directs Stop Use of AN/PRM-10 Test Oscillator Set

Sunday, August 30th, 2026

BARKSDALE AIR FORCE BASE, La. —  

Air Force Global Stike Command has directed units within the command to stop use of the AN/PRM-10 test oscillator set, a signal generator used to examine intercontinental ballistic missile (ICBM)communications systems.

This order stems from a notification AFGSC and 20th Air Force received in August that an Airman assigned to F.E. Warren AFB discovered and was exposed to residue on a component of an AN/PRM-10 kit while performing a routine inspection. The Airman reported the issue, received medical attention, and was returned to duty with no adverse effects.

Subsequent tests on the residue confirmed the presence of polychlorinated biphenyls (PCBs), a substance commonly used in electrical devices during the time that equipment was developed to maintain the Minuteman III ICBM system.

Upon notification confirming the presence of PCBs in one AN/PRM-10 unit at F.E. Warren AFB, 20th AF directed a one-time inspection (OTI) to assess all AN/PRM-10 kits. Officials also directed updated safety warnings, precautions, and mandatory personal protective equipment requirements where legacy testers remained in use.

The OTI-directed review was completed within three days of issuance and covered the entire inventory of AN/PRM-10 kits across the command. Inspections found potential residue on six of eight AN/PRM-10 systems. Samples have been collected and are being sent for testing.

Upon receiving the OTI findings indicating the presence of potential residue on additional AN/PRM-10 kits, and as a precautionary measure while sample test results are pending, units in 20th AF are immediately stopping use of the AN/PRM-10 and transitioning from the AN/PRM-10 to a modern, PCB-free replacement tester.

“Twentieth Air Force takes the responsibility to protect our Airmen very seriously,” said Maj. Gen. Colin Connor, 20th AF commander. “As our Airmen are our greatest asset, their safety and health are my top priority.”

In addition to these measures, AFGSC and 20th AF officials are working closely with the Minuteman III systems program office to appropriately dispose of existing AN/PRM-10 kits and identify any other pieces of test equipment that may contain PCBs. 

There are no mission impacts as a result of these actions, and U.S. ICBM forces remain safe, secure, and effective to protect the U.S. homeland.

“We remain vigilant for issues like these and will continue to aggressively and immediately take the appropriate actions,” added Gen. S.L. Davis, commander of AFGSC.

This effort is the latest in a series of initiatives Air Force officials have directed, following the launch of the Missile Community Cancer Study in 2023, to review the Minuteman III system and its associated equipment to ensure a safe, hazard-free working environment for America’s ICBM force.

For more information on the Missile Community Cancer Study, please follow this link: www.airforcemedicine.af.mil/Resources/Missile-Community-Cancer-Study.

By Air Force Global Strike Command Public Affairs

See CTOMS at NTOA

Friday, August 28th, 2026

CTOMS, an industry leader in tactical medical training, equipment, rope access and medical solutions, will be exhibiting at the National Tactical Officers Association (NTOA) Law enforcement operations and Trade show, taking place from 29-30 August 2026 at the Gaylord Convention Center in Nashville, TN, USA.

Visitors to the CTOMS booth 521 will have a chance to go through medical equipment carriage and organization, new equipment developed by CTOMS and how CTOMS training pathways can enhance your medical readiness in your organization.

Discover how CTOMS can enhance your readiness. See you at booth 521.

New FDA Clearance Gives PTSD Patients More Precise, Effective Treatment Options

Sunday, August 23rd, 2026

Precision brain therapy uses new technology to target post-traumatic stress disorder at the source

HOUSTON, Texas—Approximately 17.5 veterans die by suicide every day in the United States, and 7% of veterans are diagnosed each year with post-traumatic stress disorder (PTSD). Against that backdrop, Texas A&M Health researchers are helping to advance a more personalized approach to treating the disorder.

New technology developed by Wave Neuroscience, a California-based company, in collaboration with the research team of Kenneth S. Ramos, MD, PhD, with the Texas A&M Health Institute of Biosciences and Technology, has recently received FDA clearance for a system that maps and treats the specific parts of the brain impacted by PTSD. While the results are being processed for public dissemination, the findings have demonstrated promising results to revolutionize PTSD treatment options.

PTSD is a mental health condition that can develop after exposure to an event beyond average stressors, like combat, accidents, natural disasters or other forms of violence. About 6% of people will develop PTSD symptoms in their lifetimes, with women and veterans experiencing much higher rates.

Since PTSD became an official diagnosis in 1980, the most common treatments have been talk therapy and serotonin reuptake inhibitor (SSRI) medications, such as sertraline and fluoxetine. But statistics show that those treatments don’t work for everyone.

A 2020 study reviewing medications for PTSD found that while some patients improved, many did not. Patients’ self-reported symptoms improved by 6.8 to 10.1 points, and only up to 10.9% achieved remission.

The Wave Neuroscience clinical trial revealed much more promising preliminary results, according to the company’s chief medical officer Erik Won, DO.

“In comparison to that study, our FDA trial reported a 52% reduction in symptoms, so more than a four-fold increase in efficacy,” Won said. “And more importantly, we saw 68% remission in our clinical trial. So, it’s really a quantum change, an inflection point in what we can offer to patients. From a clinical care perspective, that’s really meaningful.”

Making it personal

The treatment uses Magnetic e-Resonance Therapy (MeRT), a technology created by Wave Neuroscience that combines an electroencephalogram (EEG) with transcranial magnetic stimulation. The EEG records electrical activity of the brain, while TMS—which is already used to treat other mental health conditions—uses magnetic pulses through a coil placed on the scalp.

“Transcranial magnetic stimulation, or TMS, was previously FDA cleared for treatment-resistant depression,” Won said. “By adding an augmented AI derived multivariate algorithm, we were able to personalize protocols that received FDA clearance for post-traumatic stress disorder, which should open up market access to about 13 million people who may be struggling with PTSD.”

That personalization is at the heart of MeRT.

Ramos, a physician-scientist with decades of experience in precision medicine, focuses on treatment tailored to the specific person and ailment rather than a “one-size-fits-all” approach.

“Most clinical interventions for the treatment of PTSD do not work very well,” Ramos said. “So, this is a huge area where identifying interventions that could hopefully add quality of life to the people impacted by this disorder would be tremendously impactful.”

As a leading researcher in precision medicine, Ramos was the obvious choice for Wave Neuroscience to bring into their study, said Fred Walke, chief executive officer at the company.

TMS is typically done generically, Ramos explained, but MeRT takes it one step further by customizing it to the person being treated.

Each of us is 99.9% the same, but the 0.1% difference among us dramatically changes the picture. By tailoring the treatment to the individual, the researchers were able to work with that person’s brain specifically and demonstrate significant decreases in severity of PTSD symptoms.

Ramos compared the two treatments to fixing a leaky roof: TMS, he said, is like putting a tarp over the leak to address the symptoms, while MeRT is more targeted, akin to replacing the broken shingles and addressing the problem at its source.

Breaking the mold

The path to FDA clearance began in 2024, when MeRT received the FDA breakthrough design designation, said Rick Silva, PhD, executive director of clinical trials at the Institute of Biosciences and Technology.

This designation provides an expedited pathway for FDA review. Strict scientific and medical guidelines still must be met, but the designation can reduce some of the administrative tasks that can delay getting treatments to patients.

Reaching the final stages of FDA clearance is a time-consuming and rigorous task, but for those involved, it’s all worth it.

This project, Silva said, was especially gratifying because it began during the COVID-19 pandemic and moved very quickly for an FDA clearance. While medical device clinical trials typically take around a decade to complete and gain FDA clearance, this was done in just over two years, he said.

The rigor it takes to succeed in this space reflects the expertise and talent of the Wave Neuroscience team, and it could not have been done without them, he added.

“I’ve been involved in probably close to 1,000 projects in academic medical centers over the years at varying degrees of depth and detail,” Silva said. “Patients are why I do what I do. It’s hard, and the failure rate is high, and it’s a lot of work. But when you get to a point where something is going to benefit patients, it’s very professionally gratifying and personally gratifying in many ways as well.”

For Israel Liberzon, MD, distinguished professor in psychiatry and behavioral sciences at the Texas A&M Naresh K. Vashisht College of Medicine, the clearance represents an important addition to the PTSD treatment landscape.

Liberzon served as the lead psychiatrist and PTSD expert for the study. He said once this treatment gets to patients, it will be the only non-medication treatment option for PTSD cleared by the FDA.

“Right now, the FDA has approved only two medications for PTSD,” Liberzon said. “It doesn’t mean that only two of them are used, but both are SSRIs. This is the first time that in addition to the medication, we have a non-medication option. There is psychotherapy that people use for PTSD, but psychotherapies require a lot of effort. People must participate actively, and many drop out because it’s too anxiety provoking. So now we have a unique alternative.”

The MeRT clinical trial involved five sessions per week over five to six weeks. The beneficial effects appear to be long-lasting beyond the termination of treatment.

“People living with PTSD have been left with trial-and-error treatment, medications and their side effects, and limited outcomes—even when treated by the most dedicated and experienced physicians,” Won said. “Wave’s FDA clearance signals a fundamentally different future: one in which PTSD can be objectively evaluated, precisely treated and meaningfully healed.”

The technology could eventually have applications beyond PTSD, Won said, including depression, anxiety and other conditions.

Hope on the horizon

For Leslie S. Prichep, PhD, chief scientific officer of Wave Neuroscience, the clearance signals a new era for mental healthcare.

“The FDA clearance of the MeRT System reflects decades of scientific research using electrophysiological biomarkers in identifying abnormal brain activity profiles and guiding personalized intervention strategies,” Prichep said. “We believe this represents an important advancement toward a more objective, data-informed model of mental healthcare.”

Walke said this alternative provides hope to those struggling with PTSD and their loved ones. He also hopes the more individualized approach will help reduce the stigma around mental health, as treatment becomes like putting a cast on a broken bone.


“One of the goals of the company is to create a platform for mental healthcare that uses objective imagery to help patients understand why they’re experiencing life the way that they are,” Walke said. “That insight, compounded with proven technologies, promises incredibly high efficacy when personalized.”

Alongside Texas A&M Health, Wave Neuroscience is working with key stakeholders to broaden access to the treatment and ensure it is affordable for patients through insurance coverage.

“Our hope is that this research and technology can be a catalyst for more widespread development and innovation of more effective, personalized and precision-guided treatments,” Won said. “This is proof positive that population-scale personalized medicine is not just an aspirational goal but is an achievable reality today.”

The MeRT team brings together decades of expertise spanning disciplines and technology, all with the goal of reducing suffering for people living with PTSD. FDA clearance brings them one step closer to that goal.

“Texas A&M has a very rich history of military and veteran priorities,” Ramos said. “It’s a no-brainer that Texas A&M faculty would be interested in and supportive of an initiative that hopefully would bring positive solutions to a big problem. And anything we could do to help alleviate that problem is going to go a long way towards making a difference in the individual’s life as well as the people who are close to them. I feel very fortunate that we at Texas A&M were meaningfully involved in this project.”

By LASHA MARKHAM for VITAL RECORD